Labs & Reports · Urine culture
Urine Culture Test: How to Read the Report, CFU and Growth
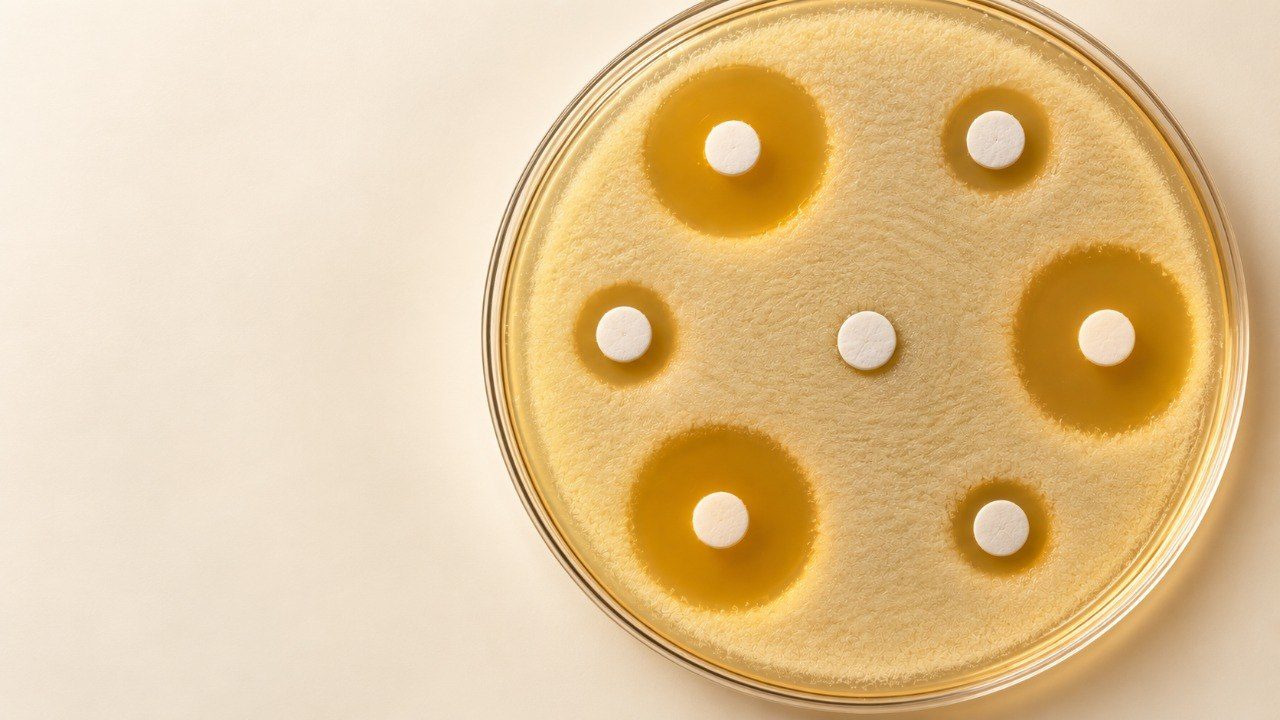
A urine culture grows whatever bacteria are in your urine so the laboratory can name the organism and find out which antibiotics still kill it. Results take 24 to 72 hours. Your report answers three questions. Did anything grow, how much of it grew, and what still works against it.
One figure on that report causes most of the confusion. Laboratories print 100,000 CFU/mL as the threshold for significant bacteriuria, and readers take it as the line between infected and clear. In a woman with burning and urgency, that line misses about half of real infections.
Quick facts
- A urine culture names the bacterium and tests antibiotics against it. A urine routine test can do neither.
- Final results take 24 to 72 hours. A negative result is often released at 24 to 48 hours.
- 100,000 CFU/mL is the classic threshold. In premenopausal women with cystitis symptoms, E. coli at 100 CFU/mL predicted bladder infection 93% of the time.
- Mixed growth is not automatically contamination. In that same group, E. coli inside mixed growth predicted true bladder infection in 91% of episodes.
- Of urinary E. coli in India's national surveillance for July to December 2025, 73% resisted ciprofloxacin. Nitrofurantoin resistance has climbed from 9% in 2022 to 21%.
- Bacteria in urine without symptoms usually need no antibiotic, except in pregnancy and before certain endoscopic urological procedures that breach the lining.
What a urine culture test measures Copy link
A urine culture test measures whether bacteria grow from your sample, which species they are, and how many of them sit in each milliliter. The laboratory spreads a measured drop of urine on agar, a nutrient jelly, and holds it at body temperature overnight. Anything alive multiplies into visible dots called colonies.
Each dot is counted as one colony-forming unit, which may have grown from a single bacterium or from a small clump of them. Counting the colonies and scaling up by the size of the drop gives colony-forming units per milliliter, written CFU/mL. That is the number printed on your report.
Unsurprisingly, E. coli accounts for most of what grows, because the organism behind the majority of urinary infections already lives in the bowel and has only a short distance to travel.
A urine routine test does a different job. It reads your urine under a microscope and with a chemical strip, reporting white cells, nitrites and protein within a few hours. It can point towards infection. Naming the organism and testing drugs against it needs a culture, which is the same method that makes blood culture the test that confirms typhoid.
Unlike most lab tests, a urine culture has no reference range. The answer is the name of an organism.
How to read a urine culture report, line by line Copy link
Read your urine culture report in four lines. The growth line says whether anything grew. The organism line names it. The colony count gives the CFU/mL. The sensitivity list shows which antibiotics were tested and how your organism responded.
Look at the organism name before you look at the count. In practice the name settles more of the question than the number does, which surprises people who were taught to read the count first and to treat everything under 100,000 as clear.
| Line on the report | What it tells you |
|---|---|
| No growth, or sterile | Nothing the laboratory counts as a urinary pathogen grew after incubation. |
| Organism isolated | The species that grew. As most people expect, E. coli tops that list, followed by Klebsiella and Enterococcus. |
| Colony count, CFU/mL | How densely that organism grew. Read this next to your symptoms. |
| Mixed growth, or mixed flora | More than one organism grew. Sometimes contamination, sometimes not. |
| Sensitivity, marked S, I or R | Which antibiotics stop this organism, and which it shrugs off. |
Wording differs between laboratories more than the underlying method does. Some print the count as a number, some as a band such as 104 to 105, and some report only that growth was significant. Check your own report against the wording in that table.
Does 100,000 CFU/mL mean you have an infection? Copy link
Not by itself. The 100,000 CFU/mL threshold was worked out on people who had bacteria in the urine without symptoms, where its job was to separate real bacteriuria from a contaminated sample. Applied to someone with acute burning and urgency, it performs poorly.
In a 1982 study of acutely dysuric women, the 100,000 CFU/mL criterion identified only 51% of those whose bladder urine actually contained coliforms. The best criterion was 100 CFU/mL, with a sensitivity of 0.95 and a specificity of 0.85.
A 2013 study repeated that comparison in 202 paired specimens from healthy premenopausal women with acute cystitis, using urine taken directly from the bladder by catheter as the reference. E. coli in midstream urine at 100 CFU/mL predicted bladder infection with a positive predictive value of 93%.
The threshold has survived in laboratory practice for six decades, partly because it still does the job it was first designed for. One round number is also far easier to print on a form than a rule that shifts with the patient in front of you.
Laboratories differ in how they handle low colony counts, and some report growth below their routine threshold as insignificant or leave it off the report altogether. In someone with symptoms, a low-count E. coli can still matter. Ask what threshold your laboratory uses.
Both studies enrolled women with acute uncomplicated cystitis, and the low threshold belongs to that situation. Men, pregnancy, children, indwelling catheters, kidney involvement and recurrent complicated infection are each read against different cut-offs.
What a normal urine culture report says Copy link
A normal urine culture report says no growth, or sterile, after 24 to 48 hours of incubation. That is the clean negative. Other wordings carry different meanings and separate usefully. Low colony count, or insignificant growth, means organisms did grow but stayed under the laboratory's reporting threshold, which can still matter if you have symptoms and the organism is a urinary pathogen. Mixed flora, or normal urethral flora, usually points to contamination or colonization instead of one dominant organism.
A negative result still helps when you feel unwell. It moves attention towards other causes of the same symptoms, such as irritation of the urethra, a vaginal infection, bladder pain syndrome, or an organism that a routine culture does not grow.
A negative culture in someone who feels well closes the matter, while a negative culture in someone with real symptoms opens a different question about what else could be producing them.
Tell your doctor if you took any antibiotic in the days before giving the sample. Even one or two doses can suppress growth enough to turn a true infection into a negative report. An antibiotic taken shortly beforehand is one reason a culture comes back empty in someone who clearly has an infection, which is why that question tends to get asked before any other.
Does mixed growth mean the sample was contaminated? Copy link
Sometimes, and less often than the phrase implies. Mixed growth means more than one organism grew. Skin and vaginal bacteria entering the container during collection explains many of these reports, which is why laboratories often ask for a repeat sample.
The 2013 catheter-paired study, run in premenopausal women with cystitis, complicates that habit. E. coli found inside mixed growth in midstream urine still predicted true bladder infection in 91% of episodes, so E. coli reported within a mixed picture is not safely treated as dirt.
The reverse held too. Enterococci and group B streptococci in midstream urine failed to predict bladder infection at any colony count at all. Among 41 episodes where one of those grew, catheter urine grew E. coli in 61% of them.
That finding belongs to the same group of otherwise healthy women. Group B streptococcus in the urine is read quite differently in pregnancy, where it carries its own implications and is acted on.
A laboratory reporting enterococcus at a high count and E. coli at a low one is describing a picture in which the low-count organism is the more likely cause of how you feel. Read both together.
The practical cost of treating every mixed report as dirt is that some people with a real infection are sent away to produce another sample, and remain untreated three days later.
So the name of the organism carries as much weight as the size of the count. Mixed growth with E. coli alongside clear urinary symptoms deserves a conversation before an automatic repeat.
Reading the sensitivity list: S, I and R Copy link
The sensitivity list names every antibiotic the laboratory tested against your organism and marks each one S, I or R. What those letters mean depends on the standard your laboratory follows, so read the legend printed on your own report. S means the organism is susceptible at a standard dose. R means resistant.
The middle letter is the one that changed. Under EUCAST, I no longer reads as intermediate at all, and now means susceptible when exposure is increased, either through a higher dose or because the drug concentrates at the site of infection. CLSI keeps an intermediate category and adds separate interpretations for urine. Indian laboratories reporting into the national surveillance network work to CLSI.
One common method is simple to picture. In disc diffusion, paper discs loaded with antibiotic sit on a lawn of your bacteria, and the laboratory measures the clear ring where growth has stopped. That measurement is then read against breakpoints set for your particular organism and drug, and the breakpoint decides the letter. Other laboratories work from the minimum inhibitory concentration, the lowest drug level that stops growth, or use automated systems.
A drug marked S is not automatically the right treatment, and one marked I is not automatically unusable. The choice also turns on whether the infection sits in the bladder or has reached the kidney, what concentration the drug achieves there, pregnancy, kidney function, allergy, what you have already taken and local prescribing guidance.
Why the sensitivity list carries more weight in India Copy link
Because the antibiotics most often reached for first now fail against most urinary E. coli here. India's national surveillance bulletin for July to December 2025 reported 34,122 E. coli isolates from urine. Ciprofloxacin failed against 73% of them. Co-trimoxazole failed against 54%.
Fosfomycin held its ground at 5%. Nitrofurantoin remains far ahead of ciprofloxacin, though it is moving the wrong way, and the surveillance record tracks the climb plainly, from 9% resistance in 2022 to 19% across 2024, 20% in the first half of 2025 and 21% in the second. That gap still matters. It is also narrowing.
Surveillance of this kind exists because somebody has to know what the opening guess should be. Where the same handful of antibiotics is prescribed millions of times a year, that answer moves faster than textbooks can follow.
Take those figures as a picture of a laboratory network. That bulletin drew on 62 government medical college laboratories along with 29 state surveillance laboratories, 20 of which are private. NCDC points out that samples reaching government medical colleges come mostly from admitted patients, or from infections that have already failed first-line treatment, which pushes the resistance figures upward.
Even so, outpatients made up the largest group in that urinary E. coli data, at 17,768 isolates against 14,394 from inpatients and 1,959 from intensive care. Among the outpatient isolates, ciprofloxacin resistance was 68% and nitrofurantoin 17%. The direction still holds. A prescription written on the first day of symptoms is a reasonable guess made without information, and the culture that lands two days later is the first point at which anyone knows whether that guess was right.
A positive culture does not always mean antibiotics Copy link
Bacteria growing in your urine while you have no urinary symptoms is called asymptomatic bacteriuria, and most of the time it needs no treatment. The 2019 Infectious Diseases Society of America guideline recommends screening for it and treating it in pregnancy, and before an endoscopic urological procedure that breaks the lining. Those are the two situations it names.
The same guideline recommends against screening or treating it in healthy non-pregnant women, in older adults, in people with diabetes, in people with long-term catheters, and in kidney transplant recipients more than a month past their transplant. For that first month the panel found the evidence too thin to recommend either way.
Somewhere between 1% and 5% of healthy premenopausal women carry bacteria in the urine at any moment. In one trial cited in that guideline, treating such women with a week of nitrofurantoin made no difference to how many developed a urinary infection over the following year.
Treating bacteria that are sitting harmlessly in the bladder exposes someone to the side effects of an antibiotic and nudges the organisms around them towards resistance, without changing how that person feels.
Diabetes does raise the risk of urinary infection. A first infection in an adult is a sensible moment to look at blood sugar control if nobody has checked it recently.
How to give a sample the laboratory can use Copy link
Catch urine from mid-flow into a sterile container, then follow the transport instructions your own laboratory gives you. An unpreserved sample generally needs to reach the bench within about one to two hours. Past that it should be refrigerated or collected into a preservative tube. Those steps are the ones the evidence supports.
A systematic review run under the United States Centers for Disease Control pooled the trials on cleaning beforehand. In women, contamination rates came out no different whether they cleaned first or not, and the reviewers graded that body of evidence as high strength. In men, catching midstream cut contamination by 77% against catching the first part of the stream, also graded high. In children, cleaning did reduce contamination.
Cleaning beforehand has held its place in collection instructions for decades, though in adult women the pooled trials found it changed nothing at all, and in children the same review found it helped.
Delay does more damage than technique. Urine held at room temperature pushed about 11% more samples past the significance line by four hours, and 137% more by 24 hours. By 48 hours the figure reached 187%. Refrigeration or a boric acid transport tube holds a sample steady for roughly a day.
Contamination stays common even when everything is done properly. Across surveyed laboratories the median contamination rate sat at 15%, while the worst tenth ran at 42%.
How long a urine culture takes, and what it costs Copy link
A result that takes three days feels slow when you are unwell, though the delay is the same biology that lets the laboratory tell one organism from another and test each drug against it separately.
The wait is biological. Bacteria need time to divide into colonies large enough to see, to identify, and then to expose to a panel of antibiotics one at a time.
A urine culture takes 24 to 72 hours. Growth becomes visible somewhere around 18 to 24 hours, and identifying the organism plus running the sensitivity panel adds another 24 to 48 hours on top. A negative result often arrives sooner, at 24 to 48 hours, because there is nothing left to identify.
The urine culture test price in India depends on the laboratory and the city more than on the test itself, and urine test cost varies most between a small standalone laboratory and a large national chain. Metropolis lists culture and sensitivity on urine at ₹750 in Delhi, ₹960 in Bengaluru, ₹1,150 in Pune and ₹1,200 in Mumbai. Redcliffe Labs lists ₹699. Aggregator listings for smaller laboratories start near ₹160.
Sensitivity testing is normally bundled into the price of the culture, which is why the test is usually ordered as urine culture and sensitivity, or urine C/S. A full body checkup package generally covers a urine routine test rather than a culture, so a culture usually has to be asked for.
When to see a doctor Copy link
Do not wait overnight. Seek care the same day for fever, shaking chills, pain in the flank or lower back, vomiting, or visible blood in the urine. Fever alongside flank pain or feeling unwell all over can mean the infection has reached the kidney, which is treated far more urgently than cystitis. Visible blood needs looking at too, though by itself it does not tell you where the infection sits.
Move faster if you are pregnant, if you have diabetes, if you are on chemotherapy or steroids, or if you have a urinary catheter in place. A rising white cell count alongside fever supports an infection that is spreading.
Recurrent infection is the situation in which a culture earns its cost most plainly, because a pattern running across several reports tells a doctor something that no single report on its own can.
What that pattern shows matters more than any single result. Whether the same organism keeps coming back, whether treatment cleared it, and whether anything points to a complicated infection. Most women with recurrent uncomplicated cystitis need no routine imaging and no cystoscopy, and the 2025 AUA guideline says so in those words for the otherwise healthy patient.
Imaging and urological assessment come in when something asks for them, such as stones or obstruction, poor bladder emptying, blood in the urine that persists, repeated kidney infections, an unusual organism, or the same organism relapsing after treatment. Kidney function tests are part of that workup rather than a routine step.
Frequently asked questions Copy link
What is a urine culture test?
A urine culture test grows the bacteria present in a urine sample so the laboratory can identify the species and test antibiotics against it. It helps confirm a urinary tract infection and name its cause when read alongside your symptoms. Results take 24 to 72 hours, since the organisms must multiply first.
How do you read a urine culture report?
Read four things. Whether anything grew, the name of the organism, the colony count in CFU/mL, and the susceptibility panel marked S, I and R. What those letters mean depends on the laboratory standard, so read your report's legend. Under EUCAST, I means susceptible at increased exposure instead of intermediate.
Does 100,000 CFU/mL always mean an infection?
No. In the study that tested it, the 100,000 CFU/mL threshold identified only 51% of women with proven bladder infection. In premenopausal women with cystitis symptoms, E. coli at 100 CFU/mL predicted bladder infection 93% of the time. Counts are read next to symptoms.
What does mixed growth mean in a urine culture?
Mixed growth means more than one organism grew, which often reflects skin or vaginal bacteria entering the sample. It is not always contamination. In premenopausal women with cystitis, E. coli appearing within mixed growth still predicted genuine bladder infection in 91% of episodes in one catheter-controlled study.
How long does a urine culture test take?
A urine culture takes 24 to 72 hours in total. Visible growth appears at roughly 18 to 24 hours, and identifying the organism plus antibiotic sensitivity testing adds a further 24 to 48 hours. A no-growth result is often issued earlier, at 24 to 48 hours.
Where is a urine culture test done?
Most diagnostic laboratories run urine cultures, and a doctor's request slip is usually all that is needed. For anyone looking for a urine culture test near me, Metropolis and Redcliffe Labs both list home sample collection across major Indian cities. Home collection saves the travel, though it makes prompt transport back to the laboratory more important.
What is the price of a urine culture test in India?
Listed prices run from about ₹160 at smaller laboratories to ₹1,200 at large chains. Metropolis lists ₹750 in Delhi and ₹1,200 in Mumbai. Redcliffe Labs lists ₹699. Antibiotic sensitivity testing is normally included in that price.
References Copy link
- Stamm WE, Counts GW, Running KR, Fihn S, Turck M, Holmes KK. Diagnosis of coliform infection in acutely dysuric women. N Engl J Med. 1982;307(8):463–468. doi:10.1056/NEJM198208193070802
- Hooton TM, Roberts PL, Cox ME, Stapleton AE. Voided midstream urine culture and acute cystitis in premenopausal women. N Engl J Med. 2013;369(20):1883–1891. doi:10.1056/NEJMoa1302186
- Nicolle LE, Gupta K, Bradley SF, et al. Clinical Practice Guideline for the Management of Asymptomatic Bacteriuria: 2019 Update by the Infectious Diseases Society of America. Clin Infect Dis. 2019;68(10):e83–e110. doi:10.1093/cid/ciz021
- Urine Culture. In: StatPearls. Treasure Island (FL): StatPearls Publishing. NCBI Bookshelf NBK557569.
- LaRocco MT, Franek J, Leibach EK, et al. Effectiveness of Preanalytic Practices on Contamination and Diagnostic Accuracy of Urine Cultures: a Laboratory Medicine Best Practices Systematic Review and Meta-analysis. Clin Microbiol Rev. 2016;29(1). doi:10.1128/CMR.00030-15
- Semi-Annual Bulletin, National Antimicrobial Resistance Surveillance Data, Issue 06, July – December 2025. National Programme on AMR Containment, National Centre for Disease Control, Directorate General of Health Services, Ministry of Health & Family Welfare, Government of India; 31 March 2026. Table 4, resistance profile of Escherichia coli; Figure 10, urinary isolates by location type.
- Semi-Annual Bulletin, National Antimicrobial Resistance Surveillance Data, Issue 05, January – June 2025. National Centre for Disease Control, Ministry of Health & Family Welfare, Government of India; 30 September 2025. Table 4, resistance profile of Escherichia coli; Figure 10, urinary isolates by location type.
- Annual Report, National Antimicrobial Resistance Surveillance Network (NARS-Net). Reporting period: January – December 2024. National Centre for Disease Control, Ministry of Health & Family Welfare, Government of India. Table 8, resistance profile of Escherichia coli.
- Definition of S, I and R. European Committee on Antimicrobial Susceptibility Testing (EUCAST).
- Recurrent Uncomplicated Urinary Tract Infections in Women: AUA/CUA/SUFU Guideline (2025). American Urological Association, Canadian Urological Association and Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction.
- Metropolis Healthcare. Culture & Sensitivity, Aerobic bacteria, Urine: city price pages for Delhi, Mumbai, Bengaluru and Pune. Redcliffe Labs, Culture Aerobic Urine Automated. Accessed 14 September 2026.
This article is for information and does not replace a consultation. Treatment for a urinary tract infection is decided by a registered medical practitioner who can see your symptoms and your report together. Sapiens is operated by Pangaea Sciences Private Limited, Hyderabad. Report an error on this page.
Written by Dr. Tarun Reddy, MBBS · Registered medical practitioner (TSMC/FMR/36195) at Sapiens, Hyderabad · Profile · Published 14 September 2026 · Editorial standards · Report an error on this page